

"your child passed the vision screening at the pediatrician's office, so their eyes are fine, right?"
A screening at the pediatrician’s office is a useful check. It does not answer every question about your child’s prescription or how quickly it is changing. If you have noticed squinting, a stronger prescription or trouble seeing at school, bring those observations to the conversation even after a passing result.
Myopia means nearsightedness. In children, it can progress as the eyes grow, so care may involve both correcting the blur and trying to slow further change. Families in Fayetteville, Fort Liberty and Hope Mills can start by asking their pediatrician how to arrange an eye examination with someone who manages childhood myopia.
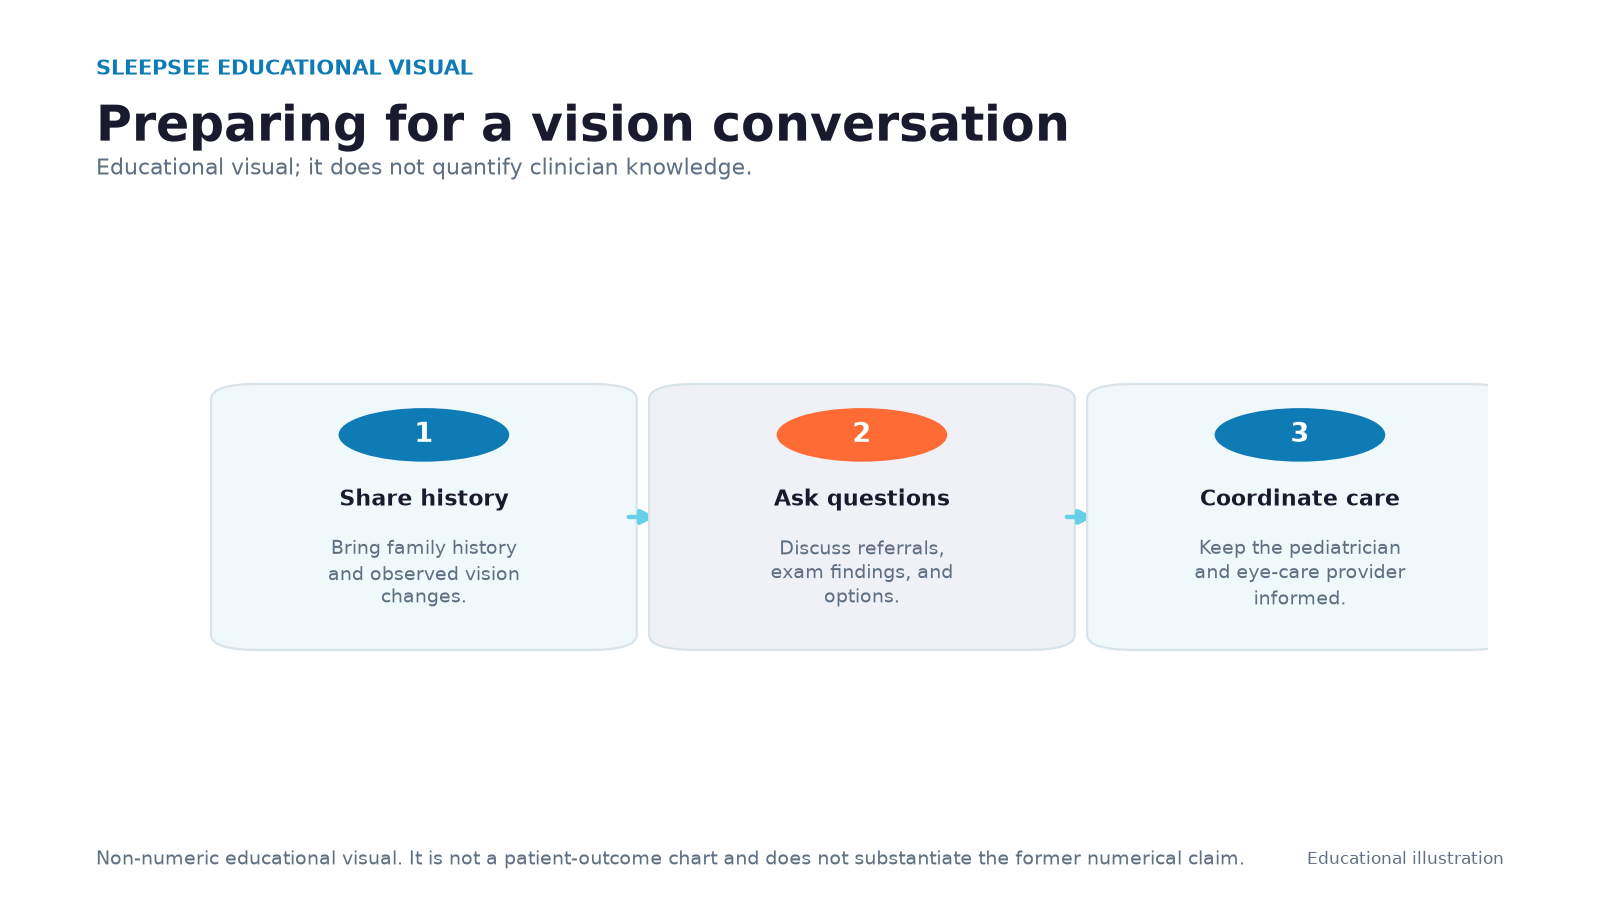
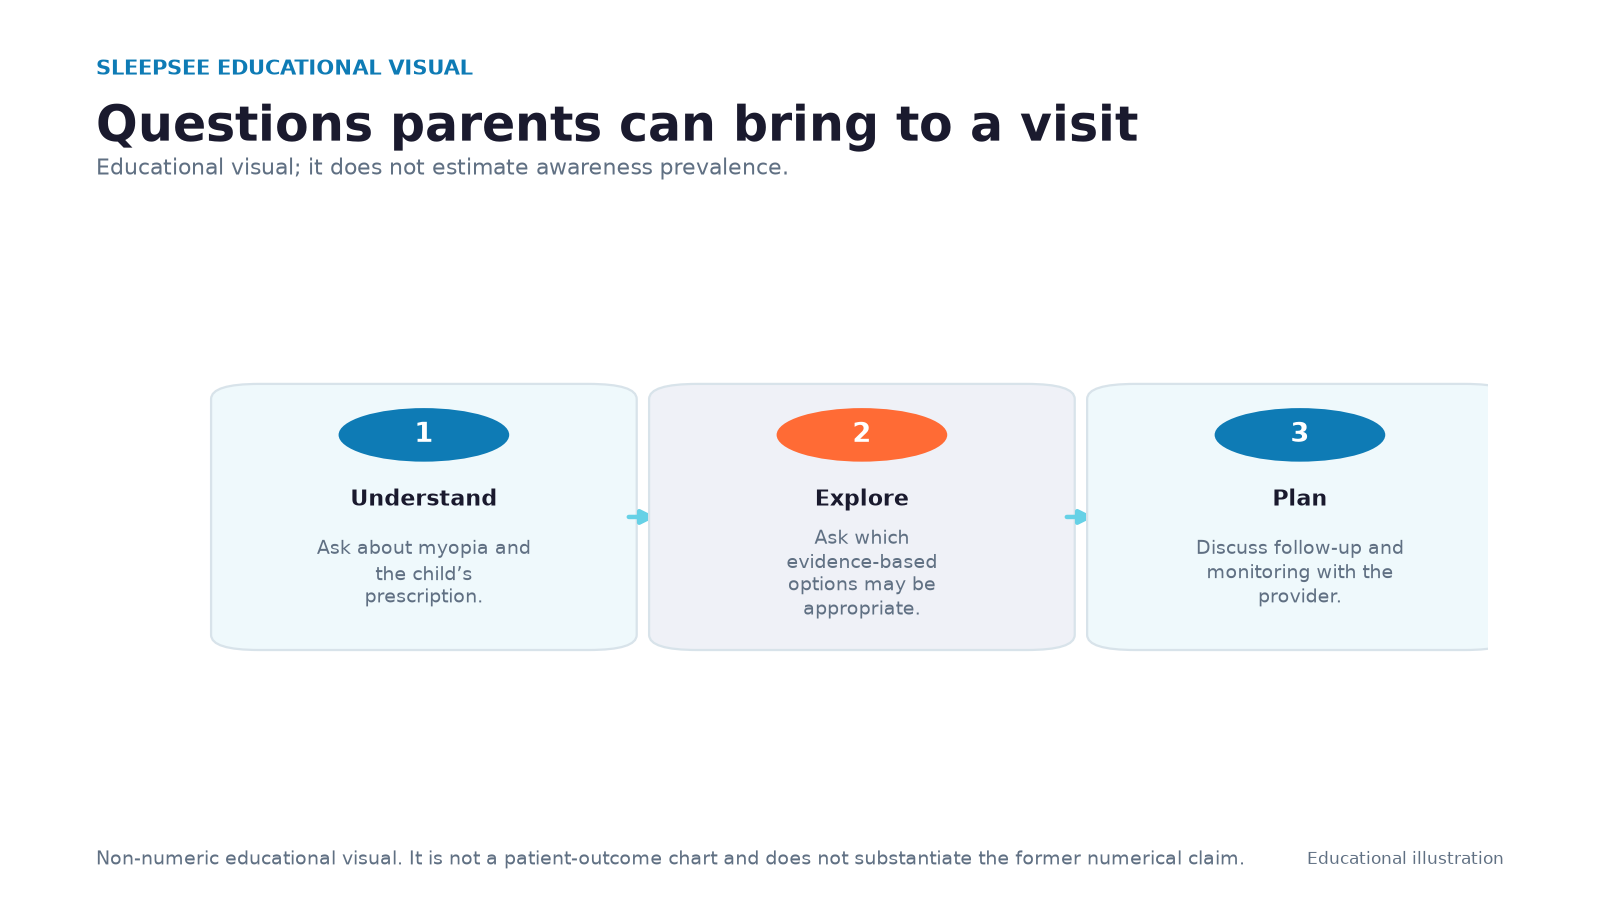
Your pediatrician can help coordinate care. An eye doctor can assess the prescription, eye health and myopia progression in more detail. The questions below can help you explain your concerns and decide who to see next.
Why Your Pediatrician Might Not Bring Up Myopia Control
Let me be clear: pediatricians are heroes. They manage everything from ear infections to growth spurts, and they do it for hundreds of patients. But the field of myopia control is a highly specialized area of optometry that is evolving at lightning speed. Frankly, it's hard for even dedicated eye doctors to keep up.
Think about it. The standard of care for myopia for decades was simply "stronger glasses." The idea of actively controlling the progression of nearsightedness is relatively new. Many medical school curriculums haven't caught up. Research shows there's a significant knowledge gap among general practitioners when it comes to the latest myopia treatments.
This isn't a knock on your doctor. It's the reality of a healthcare system where specialties are becoming more and more focused. Your pediatrician is an expert in general child health; they aren't expected to be an expert in advanced contact lens designs or the pharmacology of atropine eye drops. That's my job.
The "New" Normal: A Myopia Epidemic
It feels like everywhere you look, a child is wearing glasses. You're not imagining it. Just a generation ago, myopia was far less common. Today, it's a full-blown public health issue. By 2050, it's projected that half the world's population will be myopic. We're seeing it right here in Cumberland County schools. More kids getting glasses, and at younger and younger ages.
Why does this matter? Because high myopia isn't a benign condition. It's not just an "inconvenience." The more a child's eye grows and their prescription increases, the higher their risk for serious, sight-threatening diseases later in life, like retinal detachments, glaucoma, and myopic maculopathy. This isn't a scare tactic; it's a scientific fact backed by decades of research. You can read more about the specifics in my article on the childhood myopia epidemic.

This is why proactive myopia management is so critical. We have a window of opportunity during childhood and adolescence to slow down the runaway train of prescription changes. But it starts with awareness.
How to Prepare for the Conversation
Walking into your pediatrician's office armed with information is the best way to turn a routine check-up into a productive consultation. You become an advocate for your child's health.
-
Do Your Homework. Before the appointment, read up on myopia management from reliable sources. High-authority websites like the American Academy of Ophthalmology (AAO) or the National Center for Biotechnology Information (NCBI) are great places to start. Understand that myopia control is not about reversing nearsightedness, but about slowing its progression.
-
Track the Signs. Is your child squinting to see the board at school? Holding their tablet super close to their face? Complaining of headaches? These are classic symptoms. I outline more of them in my article on the 5 signs your child might need myopia control. Jot down your observations and bring them with you.
-
Frame Your Questions. Instead of asking, "Is your child nearsighted?" try a more proactive approach. You're not just asking for a diagnosis; you're opening a dialogue about long-term strategy.
Key Questions to Ask Your Pediatrician
Here’s a list you can take right into the exam room. Don't be shy about having your notes out. This is your child's future vision we're talking about.
- "I have noticed my child is [describe the change, such as squinting]. Could this be a vision problem?"
- "Both parents are nearsighted. Does that change when our child should have an eye examination?"
- "How can we find out whether the prescription is getting stronger?"
- "Could myopia management, such as Ortho-K or atropine, be appropriate?"
- "Who would you recommend for an assessment of myopia progression?"
Listen to their answers. A good pediatrician will take your concerns seriously. They may not have all the answers, but they should be supportive of you seeking a specialist's opinion. If you get a dismissive response, like "We'll just get them stronger glasses when they need them," that's a red flag. It's an outdated approach that ignores the long-term risks.
Your Pediatrician and Your Eye Doctor: A Team Approach
The American Academy of Pediatrics (AAP) itself provides guidelines for vision health, but your pediatrician is ultimately a generalist. They are your frontline defense, but for specialized issues, they refer out. It's the same way they'd send you to an orthopedist for a complex fracture or a cardiologist for a heart murmur.
An eye doctor who manages myopia can measure more than how many letters your child reads on a chart. Corneal topography maps the front surface of the eye, and a biometer measures axial length. Repeated measurements help the doctor follow changes and discuss whether the current care plan is doing enough.
A sleepSEE evaluation looks at the child’s eyes and the routine the family can manage. For suitable candidates, custom Ortho-K lenses temporarily reshape the cornea during sleep for daytime vision correction. They also change the eye’s optics in a way used to help slow myopia progression. Follow-up visits check both the fit and the child’s response.
A Note on Insurance
I believe in being upfront with families about the practical costs of care. At the founding Fayetteville location, sleepSEE program fees are private-pay; insurance and TRICARE are not accepted for those program fees. This is the practice's payment policy, not a statement that every eye examination or service has the same insurance treatment.
Cash, Visa and Mastercard are accepted, and CareCredit is available. HSA/FSA funds may be used for eligible expenses. Ask for an itemized explanation of the program, what is included during the first year and what costs may continue afterward. The current program fees and payment options give you a starting point for that discussion.
Dr. James Singletary, OD, FIAOMC
Dr. James Singletary, OD, FIAOMC is a licensed optometrist and orthokeratology specialist with over 20 years of clinical experience in myopia control, myopia management, orthokeratology, and nonsurgical vision correction. He is the founder of Eye Medics Optometry in Fayetteville, NC and the creator of the sleepSEE ortho-k program.
Medical Disclaimer
This article is for informational purposes only and does not constitute medical advice. Always consult with a qualified eye care professional for diagnosis and treatment of eye conditions. The information provided here should not be used as a substitute for professional medical advice.


